
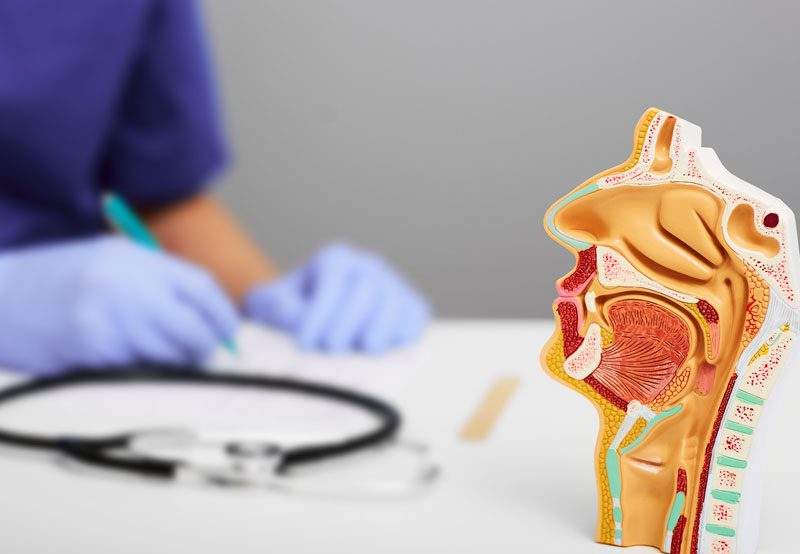
Oral cavity cancer is a malignant condition that develops in the tissues of the mouth, including the lips, tongue, gums, inner cheeks, floor of the mouth, and hard palate. The majority of oral cavity cancers are squamous cell carcinomas arising from the lining of the oral mucosa. These cancers can significantly affect speech, chewing, swallowing, and appearance, particularly when diagnosed at advanced stages. Early detection plays a critical role in improving outcomes and reducing the need for extensive surgery or reconstruction.
Causes
Oral cavity cancer develops as a result of chronic exposure to carcinogenic factors that damage the cells lining the mouth. Several well-established risk factors have been identified.
- Tobacco use: Cigarettes, cigars, pipes, chewing tobacco, and snuff are the strongest risk factors
- Alcohol consumption: Heavy alcohol use increases risk, especially when combined with tobacco
- Human papillomavirus (HPV): Less commonly involved than in oropharyngeal cancer but associated with select oral cancers
- Chronic oral irritation: Poorly fitting dentures, sharp teeth, or long-standing inflammation may contribute
- Sun exposure: A major risk factor for cancers of the lower lip
- Poor oral hygiene and nutritional deficiencies: May increase susceptibility
- Prior head and neck cancer: Raises the risk of developing a second primary tumor

Symptoms
Symptoms may be subtle in early disease and are often mistaken for benign oral conditions. Persistence is a key warning sign.
- A mouth sore or ulcer that does not heal
- Red or white patches on the gums, tongue, or lining of the mouth
- A lump, thickening, or mass in the mouth or neck
- Pain or numbness in the mouth or lips
- Difficulty chewing, swallowing, or speaking
- Loose teeth or jaw discomfort without dental cause
- Unexplained bleeding in the mouth
- Changes in speech clarity
Any oral lesion lasting longer than two weeks warrants further evaluation.
Diagnosis
Diagnosis requires careful examination of the oral cavity and assessment of disease extent.
- Comprehensive head and neck examination: Visual and tactile inspection of the mouth, tongue, and neck lymph nodes
- Biopsy: Tissue sampling of suspicious lesions to confirm malignancy
- Imaging studies: Computed tomography or magnetic resonance imaging to assess tumor depth, bone involvement, and lymph node spread
- Positron emission tomography: Used in select cases to evaluate advanced disease or distant spread
- Dental and nutritional assessment: Often performed to support treatment planning
Staging incorporates tumor size, depth of invasion, lymph node involvement, and distant metastasis.
Treatment Options
Treatment is guided by tumor location, stage, and patient-specific factors, with an emphasis on cancer control and functional preservation.
- Surgical resection: Primary treatment for most oral cavity cancers, often including removal of involved lymph nodes in the neck
- Reconstructive surgery: May involve local flaps, skin grafts, or microvascular free tissue transfer to restore speech, swallowing, and appearance
- Radiation therapy: Used after surgery in cases with high-risk features or as primary treatment when surgery is not feasible
- Chemoradiation: Reserved for advanced disease or when adverse pathologic features are present
- Rehabilitation services: Speech therapy, swallowing therapy, and nutritional support are integral to recovery
Management typically involves a multidisciplinary team to address both oncologic and functional needs.
When to See a Specialist
Evaluation by a head and neck specialist is recommended for any persistent oral lesion, unexplained mouth pain, difficulty swallowing, or neck mass. Early referral improves diagnostic accuracy and expands treatment options, often allowing for less extensive surgery and better long-term functional outcomes.